
General Services
The First 120 Hours After Unprotected Intercourse: Your Medical Emergency Action Plan
After Unprotected Intercourse
Unprotected intercourse isn't part of the plan for most women. A condom tears, a pill is forgotten, or intercourse is assumed to have "stopped in time." The next morning brings the same three questions: will I get pregnant, is the pill enough, can this be resolved without seeing a doctor.
At SoftCare Clinic, this page stands without disturbing the core of the previous text: the morning-after pill alone is not a "new miracle"; the pregnancy-prevention percentage of the systemic hormone is not as high as the posters suggest; a woman who wants to seriously rule out pregnancy comes to see a physician. What has been added is the time window, the distinction between pill types, and why the IUD — particularly the copper IUD, and in current data the 52 mg levonorgestrel Mirena — stands above the pill.
Emergency contraception does not end an established pregnancy. If the test is positive, the matter changes. Time, a negative test, and the physician's office belong in the same sentence. The physician is Op. Dr. Şükrü Sanus. The clinic is in Şişli Fulya.
How to take precautions after unprotected intercourse
The one common step a woman can take at home, without a prescription, is the morning-after pill. The pill attempts to delay ovulation. If ovulation has already occurred, or if hours have passed, its effect decreases. This is why the sentence from the previous page still stands: if avoiding pregnancy matters to you, a more serious measure is needed. That serious measure is the room with the speculum and the IUD table.
There is only one timeline. The time of intercourse is noted. The first day of the last period is asked. A urine pregnancy test is checked. If the test is negative, the emergency method is discussed; if positive, the matter of emergency contraception is closed. Infection screening is a separate matter; this page addresses pregnancy risk and does not substitute for a condom.
Timeline: how much time do you have
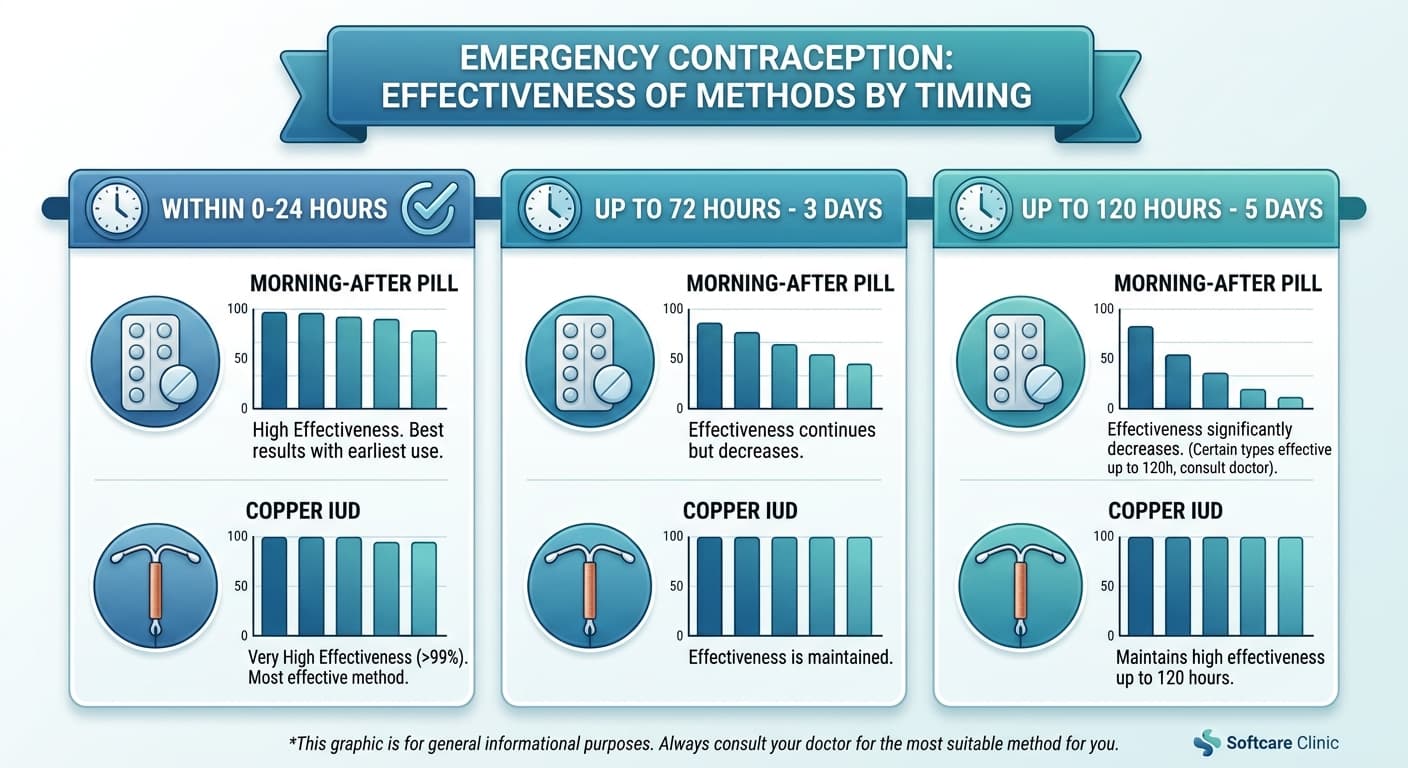
The first 24 hours
This is the golden window. The levonorgestrel pill shows its highest effectiveness in this window. An IUD can also be inserted the same day. Delaying the pill with "I'll stop by the pharmacy tomorrow" burns the advantage of the first day.
Up to 72 hours (3 days)
The licensed and practical window for classic levonorgestrel-based morning-after pills mostly falls here. As time passes, the success rate declines. Ulipristal acetate and the IUD remain effective in this window as well.
Up to 120 hours (5 days)
The effect of the standard levonorgestrel pill weakens noticeably in this range. Ulipristal acetate is discussed as the oral option. In the clinic, however, a copper IUD or the 52 mg hormonal IUD (Mirena), when inserted within 120 hours, reaches an effectiveness band the pill cannot reach. The door does not close just because five days have passed; what closes is the pill's promise, not the IUD option.
Which method is right for you
Morning-after pills
These circulate publicly as if they were a new discovery. In reality, the content is an emergency dose of a hormone obstetrics has used for years. Two active substances are common in Turkey: levonorgestrel (mostly within the first 72 hours) and ulipristal acetate (up to 120 hours). Both suppress or delay ovulation. They do not terminate an established pregnancy.
Weight, liver-enzyme-inducing medication, and the time of intercourse change the dose and the choice. If vomiting occurs within a few hours of taking the pill, the dose is discussed again. The pill does not protect subsequent acts of intercourse. A short interval may be needed before switching to hormonal contraception after ulipristal; this distinction is not something to resolve at home.
Why spermicidal douching is not a method
Spermicidal douching — rinsing the vagina and the area around the cervix with a solution — mentioned on the previous page, is a question women still ask. Current emergency contraception guidelines do not list it as a method. Sperm reaches the cervix within minutes; douching does not prevent pregnancy. Assuming douching "closed the matter" causes the real window to be missed.
The IUD: the real solution in emergency contraception
For a woman who wants to seriously rule out pregnancy, the pill is the second line. The intrauterine device is the first line. Copper ions disrupt the environment for sperm and the oocyte, making the endometrium unsuitable for implantation. The 52 mg levonorgestrel IUD uses the same window with a local hormone. Both are inserted within 120 hours, with a negative test, in suitable anatomy.
The numbers are clear. The copper IUD, used as emergency contraception, reduces the pregnancy rate to around one in a thousand. In a 2021 comparative study of the 52 mg levonorgestrel IUD, the rate was not statistically behind copper (approximately three in a thousand). The percentage figures for pills fall below this band. The sentence "the doctor definitely prevents pregnancy" is not medical; the IUD stands where the pill's promise stops.
I Had Unprotected Sex, What Should I Do?
Copper IUD (Cu-IUD)
These are the classics among the guidelines. They are inserted within five days of unprotected intercourse. If the device is left in place after the procedure, protection continues for years — up to ten years, depending on the copper model. Removal after the emergency purpose is served is not mandatory. It may increase bleeding; this is a disadvantage compared to the hormonal device. The cost is lower than the hormonal model.
Hormonal IUD — Mirena (52 mg)
Data from recent years show that copper is not the only option in the emergency window. The 52 mg levonorgestrel-releasing IUD (best known in Turkey as Mirena) has shown emergency effectiveness considered equivalent to the copper IUD. Kyleena and other lower-dose models carry no evidence for this indication; the device discussed for emergency use is the 52 mg version.
Mirena's clinical advantage is not limited to the emergency percentage. If the device remains in place after insertion, long-term protection continues. The same device is often recognized in Turkey through a different door: symptomatic treatment of heavy menstrual bleeding, provided there is no underlying structural condition. As long as it stays in the uterus, bleeding decreases significantly for most women, and in some cases menstruation nearly stops. This effect is a desired outcome for some women; for a woman who only wants "to close this one night," it may be a burden.
This is why how long a Mirena inserted for emergency purposes stays in place is a physician's decision. If a woman does not want prolonged light bleeding or amenorrhea, the device is planned for removal once the emergency window has closed; a copper IUD or another method can be placed instead. If she wants the persistent lighter bleeding, the Mirena is left in place. The removal date is not an internet-forum sentence.
The one clear disadvantage is cost. The hormonal IUD is significantly more expensive than the copper IUD. The difference in effectiveness is not marketed as "Mirena protects more"; the difference lies in the bleeding profile and the price. What is suitable is discussed in the consultation room.
A Note from Dr. Şükrü Sanus
"As the name suggests, emergency contraception methods are not a routine method of protection but a 'rescue' plan for exceptional situations. In particular, the copper IUD we use at our clinic gives excellent results for patients who do not want to use the pill, or who are past the pill's window (72–120 hours). It's important to remember that these methods do not terminate an existing pregnancy — they are not an abortion — they simply prevent a pregnancy from occurring. In this process where you are racing against time, don't hesitate to seek medical support."
Frequently asked questions
Within how many hours should the morning-after pill be taken?
As soon as possible. For levonorgestrel, the primary window is 72 hours; for ulipristal, it is 120 hours. In both cases, the first 24 hours are better.
If 72 hours have passed, is the pill useless?
Levonorgestrel weakens; ulipristal and the IUD are still discussed. The door does not close before five days have passed.
Which is the most effective emergency method?
The intrauterine device. The pill delays ovulation; the IUD changes the intrauterine environment.
Copper IUD or Mirena?
Both are highly effective within 120 hours. Copper is cheaper and may increase bleeding; Mirena is more expensive and reduces bleeding.
Does Mirena stay in place after emergency insertion?
It can stay or be removed. The decision belongs to the woman's expectations regarding bleeding and the physician's plan.
Is the pill an abortion?
No. It does not terminate an established pregnancy. If the test is positive, the matter of emergency contraception is closed.
The condom tore tonight — what should I do?
Note the time; don't wait until tomorrow morning. If a pill is to be taken, take it today; if an IUD is being considered, an appointment is made in Şişli Fulya.
Does protection continue after taking the pill?
No. The next act of intercourse in the same cycle requires separate protection.
Does the pill delay the period?
It can delay or bring it forward. A test is checked two weeks later; don't read a delay as "I was protected."
A week has passed since intercourse — can an IUD still be inserted?
The standard 120-hour window for emergency contraception has passed. What follows is a decision based on testing and examination; it is not a home solution.
Quick summary
Time matters after unprotected intercourse. The pill is the first step at home, not a miracle. Within five days, the IUD is the most reliable option: the copper IUD is the classic and more economical choice; the 52 mg Mirena carries similar emergency effectiveness, reduces bleeding, costs more, and how long it stays in place is decided with your physician. SoftCare Clinic is located in Şişli Fulya. IUD details are on the How the IUD Is Inserted page. Appointments: Book an Online Appointment.
This text is general information; it does not replace medication instructions or a diagnosis. Medical director: Op. Dr. Şükrü Sanus. Şişli Fulya · +90 212 241 30 10 · softcareclinic.com
References
- Emergency contraception (fact sheet). World Health Organization (WHO).
- Medical eligibility criteria for contraceptive use (5th edition). World Health Organization (WHO), 2015.
Medically reviewed by Op. Dr. Şükrü Sanus, Obstetrician & Gynecologist · Last medical review: